ApoB
Table of contents
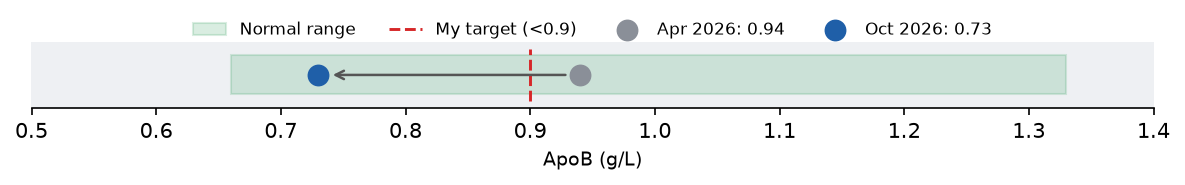
ApoB is the lipid number my doctor cares about most after LDL. Mine was just above his target in April 2026 and comfortably under it by October. This article explains what ApoB measures, why many doctors think it’s a better marker than LDL, and my Lp(a) result, which is the genetic side of the same story.
Snapshot
| April 2026 | October 2026 | Lab range | My target | |
|---|---|---|---|---|
| ApoB | 0.94 g/L | 0.73 g/L | 0.66–1.33 | <0.9 |
| ApoA1 | 1.30 g/L | 1.71 g/L | 1.04–2.02 | |
| ApoB/A1 ratio | 0.72 | 0.43 | 0.22–0.80 | |
| Lp(a) | <7.0 nmol/L | not retested | <75 | |
| Status | ⚠️ Above target | ✅ On target |
From my October report, with my doctor’s handwritten April value, tick and target next to ApoB:

What it is
Every particle that can carry cholesterol into artery walls (LDL, VLDL, IDL and Lp(a)) has exactly one ApoB protein on its surface. So measuring ApoB is a way of counting those particles.
That matters because what drives plaque is mostly the number of these particles getting into the artery wall, not just the amount of cholesterol they carry. Two people can have the same LDL cholesterol, but one has fewer, larger particles and the other has many small ones. The second person has more ApoB and, all else equal, higher risk. That’s why many lipid specialists now treat ApoB as a sharper measure than LDL.
ApoA1 is the main protein on HDL particles, the ones that carry cholesterol back to the liver. The ApoB/A1 ratio compares the harmful particles with the protective ones, so lower is better.
Lp(a), or lipoprotein(a), is an LDL-like particle with an extra protein attached. Your Lp(a) level is mostly set by your genes and barely changes with diet or exercise, so it’s usually tested once in a lifetime.
What I’m aiming for
- Lab range: 0.66–1.33 g/L. This is a population range, not a risk target.
- My doctor’s target: under 0.9 g/L, set in April.
For someone my age without heart disease, under 0.9 is a reasonable target. Lower still is generally better over a lifetime.
Why April was a problem
At 0.94 g/L, my ApoB was only slightly above target, but it lined up with LDL being over its limit (3.45) and total cholesterol flagged high. Together they said I had more cholesterol-carrying particles than ideal. Over decades, that’s what adds to plaque in the arteries and raises the risk of heart attack and stroke.
The reassuring part was Lp(a) under 7.0 nmol/L, which is very low (the lab’s limit is 75). Lp(a) is the piece of lipid risk you inherit and can’t change much. Mine being so low meant my higher ApoB was coming from things I could change.
Why October is better
ApoB dropped from 0.94 to 0.73 g/L, and my doctor ticked it. ApoA1 rose from 1.30 to 1.71, so the ApoB/A1 ratio improved from 0.72 to 0.43.
What probably helped is the same as for LDL:
- Fat loss: body fat went from 19.3% to 9.55%, and visceral fat almost halved.
- Diet: lower-GI carbs such as brown rice, and more protein.
- Much more training: BJJ built up from weekly to 6 times a week before my competition on 11 October, plus a conditioning programme.
The rise in ApoA1 matches HDL going up, which is common with more exercise and less body fat.
As with LDL, I was tested 9 days after a weight cut. A calorie deficit can lower lipid numbers for a while, so I’ll be watching whether ApoB stays under 0.9 at maintenance weight.
What’s next
- Recheck ApoB at my next blood test, ideally at a stable weight.
- Lp(a) doesn’t need retesting. Being genetic, the April result covers it.
- Keep the diet and training habits that got it here.
This is my own personal data, shared for interest only. It’s not medical advice.
Until next time, peace and love!